
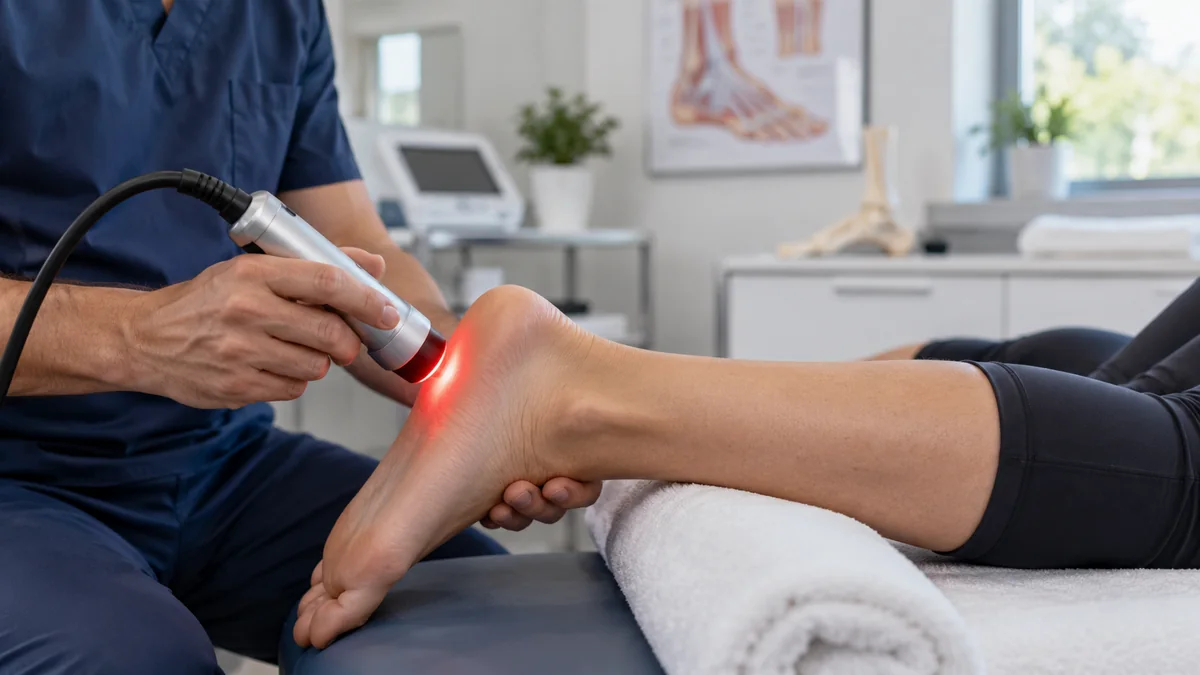
Many tendon, fascia, and superficial soft tissue targets around the foot, heel, and Achilles are anatomically suitable for laser application. In our Bodrum clinic, we consider the 980 nm laser as the primary wavelength; we evaluate 1470 nm only as an adjunct wavelength in selected, very superficial targets, taking tissue thickness and skin safety into consideration.
When can it be considered?
- Mid-portion Achilles tendinopathy
- Insertional Achilles tendon pain
- Plantar fasciitis and medial heel pain
- Superficial tendon/fascia tenderness that increases with loading
How are 980 nm and 1470 nm selected?
980 nm is the primary option in terms of clinical use and HILT literature in tendons and surrounding soft tissues. Because 1470 nm has higher water absorption, it exhibits a more superficial and thermal effect; therefore, it is used only in selected targets, taking tissue thickness and skin safety into consideration.
Scientific data
A tendinopathy meta-analysis published in 2026 reported an overall improvement in pain and disability with HILT across different tendon regions; however, the number of studies for the Achilles tendon is more limited compared to the rotator cuff and lateral epicondylitis. In plantar fasciitis, 2026 meta-analyses show that HILT can produce results similar to ESWT in terms of pain, but its functional superiority is not clear. For this reason, in plantar fasciitis as well, we position laser not as a standalone primary solution, but as an adjunct option to load management and exercise.
Our approach in our Bodrum clinic
In Achilles and plantar fascia pain, we evaluate mechanical factors such as calf strength, ankle range of motion, footwear, walking-running load, and body weight. Treatment is planned with progressive loading, calf and intrinsic foot muscle exercises, insole/footwear modification if necessary, and laser in selected patients.
When is a different evaluation required?
If there is a sudden sensation of rupture, marked loss of strength, inability to walk after trauma, signs of infection, or unexplained night pain, a diagnostic evaluation is performed first.
Return to the Laser Pain Therapy main page →
Detailed guides for foot, heel, and Achilles
- Achilles tendinopathy
- Plantar fasciitis / plantar heel pain
- Achilles paratenon pain
- Retrocalcaneal bursitis
- Pain after ankle sprain
- Peroneal tendinopathy
- Tibialis anterior tendon pain
- Tibialis posterior tendinopathy
- Metatarsalgia
- Morton’s neuroma
References
- Effectiveness of high-intensity laser therapy for tendinopathy: systematic review and meta-analysis. 2026. PMID: 41964853.
- High-Intensity Laser Therapy Versus Extracorporeal Shockwave Therapy for Plantar Fasciitis: systematic review and meta-analysis. 2026. PMID: 41596021.
- Effect of Local Laser Therapy on Plantar Fasciitis: meta-analysis. 2026. PMID: 41682989.

