What does PRP target in knee osteoarthritis?
The goal of PRP is not to “create a new joint.” It is aimed at biological mediators released from platelets modulating the intra-articular inflammatory environment and tissue response. The outcomes most frequently evaluated in clinical studies are pain, daily activity, and function scores. Data on changes in cartilage structure, on the other hand, are more heterogeneous.
In whom might it be more meaningful?
- Those with early or moderate knee osteoarthritis
- Those with persistent pain and loss of function despite conservative treatments
- Patients who can participate in an exercise and rehabilitation program
- Patients without advanced structural deformity and with limited mechanical axis deviation
In advanced-stage osteoarthritis, marked deformity, or severe mechanical problems, the expected contribution of PRP may be more limited, and surgical/orthopedic options should be evaluated separately.
In which joints is it used?
The knee is the region with the most extensive evidence. PRP has also been investigated in the shoulder, hip, ankle, and some small joints; however, the strength of evidence, application technique, and patient selection vary by region.
Why can ultrasound guidance be used?
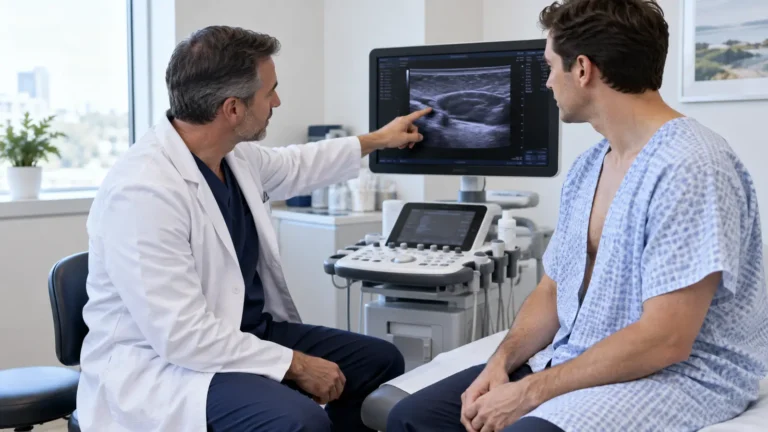
In intra-articular and periarticular injections, ultrasound can help visualize the target anatomy and plan the needle trajectory. Especially in deep joints or when there is concomitant tendon/bursa pathology, imaging guidance supports clinical evaluation.
Is PRP sufficient on its own?
No. In the management of knee osteoarthritis, muscle strength, weight control, daily load management, walking pattern, appropriate exercise, and, when necessary, physical therapy are important components. A biologic injection should be evaluated not as a replacement for the rehabilitation program, but as an option that supports it in appropriate patients.
What does current scientific evidence say?
The 2026 AAPM&R guidance document emphasizes the importance of patient selection, product characteristics, and standardization for PRP in knee osteoarthritis. Older consensus statements and meta-analyses have also reported symptomatic improvement, especially in early-to-moderate knee osteoarthritis. However, differences in PRP preparation methods across studies make direct comparison of results difficult.
Our approach at our Bodrum clinic
In knee pain, we first determine the source of the pain. The degree of osteoarthritis, meniscus, ligaments, muscle strength, tendons around the knee, and biomechanical load are evaluated together. If PRP is deemed appropriate, the product type, injection target, and subsequent rehabilitation plan are tailored to the individual.
Related pages
Related cell therapies
Cell Therapies main showcase · PRP Therapy · Differences Between PRP, SVF, and Stem Cells · Application Areas
References
- AAPM&R guidance statement on platelet rich plasma for knee osteoarthritis. 2026. PMID: 41989317.
- Intra-articular PRP in symptomatic knee osteoarthritis: consensus statement. PMID: 32583023.
Written and medically reviewed by: Dr. Kerem Çağlayan
Last medical review: September 14, 2026
Disclaimer: This content is for general health information. In any surgical or interventional procedure, outcomes may vary from person to person. It is recommended that you consult your physician for detailed advice prior to the procedure.