Key points
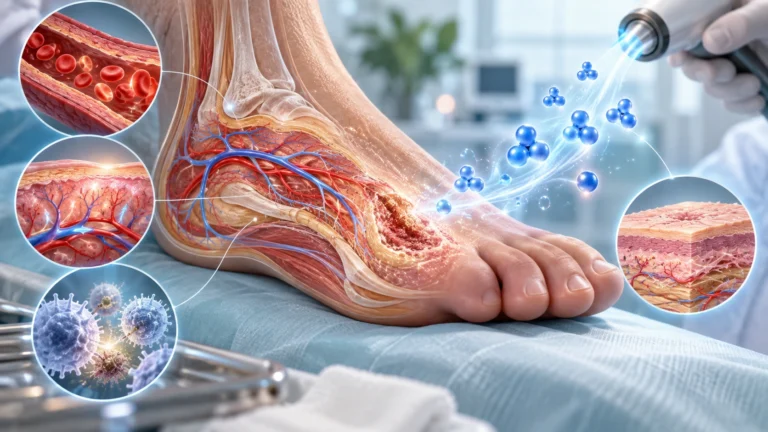
- A diabetic foot ulcer is not just a wound that forms on the skin surface; neuropathy, circulatory impairment, pressure, and infection can all play a role together.
- A non-healing wound should be evaluated for circulatory insufficiency or deep infection.
- Offloading, appropriate debridement, glucose control, and infection management are fundamental parts of treatment.
- Ozone, photobiomodulation, and other advanced modalities may provide support in some patients; the extent to which they can contribute to which patient varies according to wound type and protocol.
Why does a diabetic foot ulcer develop?
Diabetes-related nerve damage can reduce sensations of pain and pressure; repetitive loading can lead to tissue damage without being noticed. If vascular disease is also present, healing may become even more difficult. Shoe pressure, deformity, and trauma are also significant triggers.
Which findings are important?
The size and depth of the wound, necrosis, discharge, odor, surrounding erythema, pain, temperature changes, and systemic symptoms are evaluated. Pulses, capillary refill, neuropathy, and pressure points are checked.
Circulatory evaluation
Weak pulses in the foot, coldness, skin color changes, or slower-than-expected healing may warrant an arterial circulation assessment. Modalities such as ABI/TBI or Doppler are selected according to the clinical situation.
Infection and osteomyelitis
In wounds that are deep, open for a long time, or located close to bone, the possibility of osteomyelitis should be evaluated. Fever or prominent systemic findings may not always be present; if clinical suspicion exists, imaging and appropriate microbiological evaluation may be necessary.
Foundation of treatment
Offloading, wound bed preparation, appropriate dressing, glucose control, treatment of infection, and optimization of circulation constitute the fundamental approach. Advanced wound care products or adjunctive technologies are added on top of this foundational structure.
Ozone and red light/PBM
Favorable results have been reported in diabetic foot studies on ozone and photobiomodulation. However, because study quality and the protocols used vary, research is ongoing regarding the most appropriate indication and dose. These modalities should be evaluated not as a replacement for standard care, but as supportive therapies in selected patients.
When is urgent evaluation needed?
Rapidly spreading erythema, fever, foul-smelling heavy discharge, blackening, a cold foot, newly onset severe pain, or deterioration of general condition warrants urgent evaluation.
Our approach at our Bodrum clinic
We evaluate the local appearance of the wound together with circulation, neuropathy, infection, glucose control, and loading. Once the necessary standard care is established, we plan supportive therapies alongside individualized goals.
Related guides
- Chronic Wound Assessment and Wound Treatment
- Ozone: Diseases and Clinical Conditions
- Red Light Therapy and Photobiomodulation
- Insulin Resistance and Metabolic Syndrome
- Weight Management and Metabolic Health
References
- Chen P, et al. IWGDF Guidelines on interventions to enhance healing of foot ulcers in people with diabetes. 2024. PMID: 37232034.
- Silva Filho MLE, et al. Ozone therapy as a treatment for diabetic foot ulcers. 2024. PMID: 39630555.
Written and medically reviewed by: Dr. Kerem Çağlayan
Last medical review: September 10, 2026
Disclaimer: This content is not personal diagnostic or treatment advice.