
Quick Answer
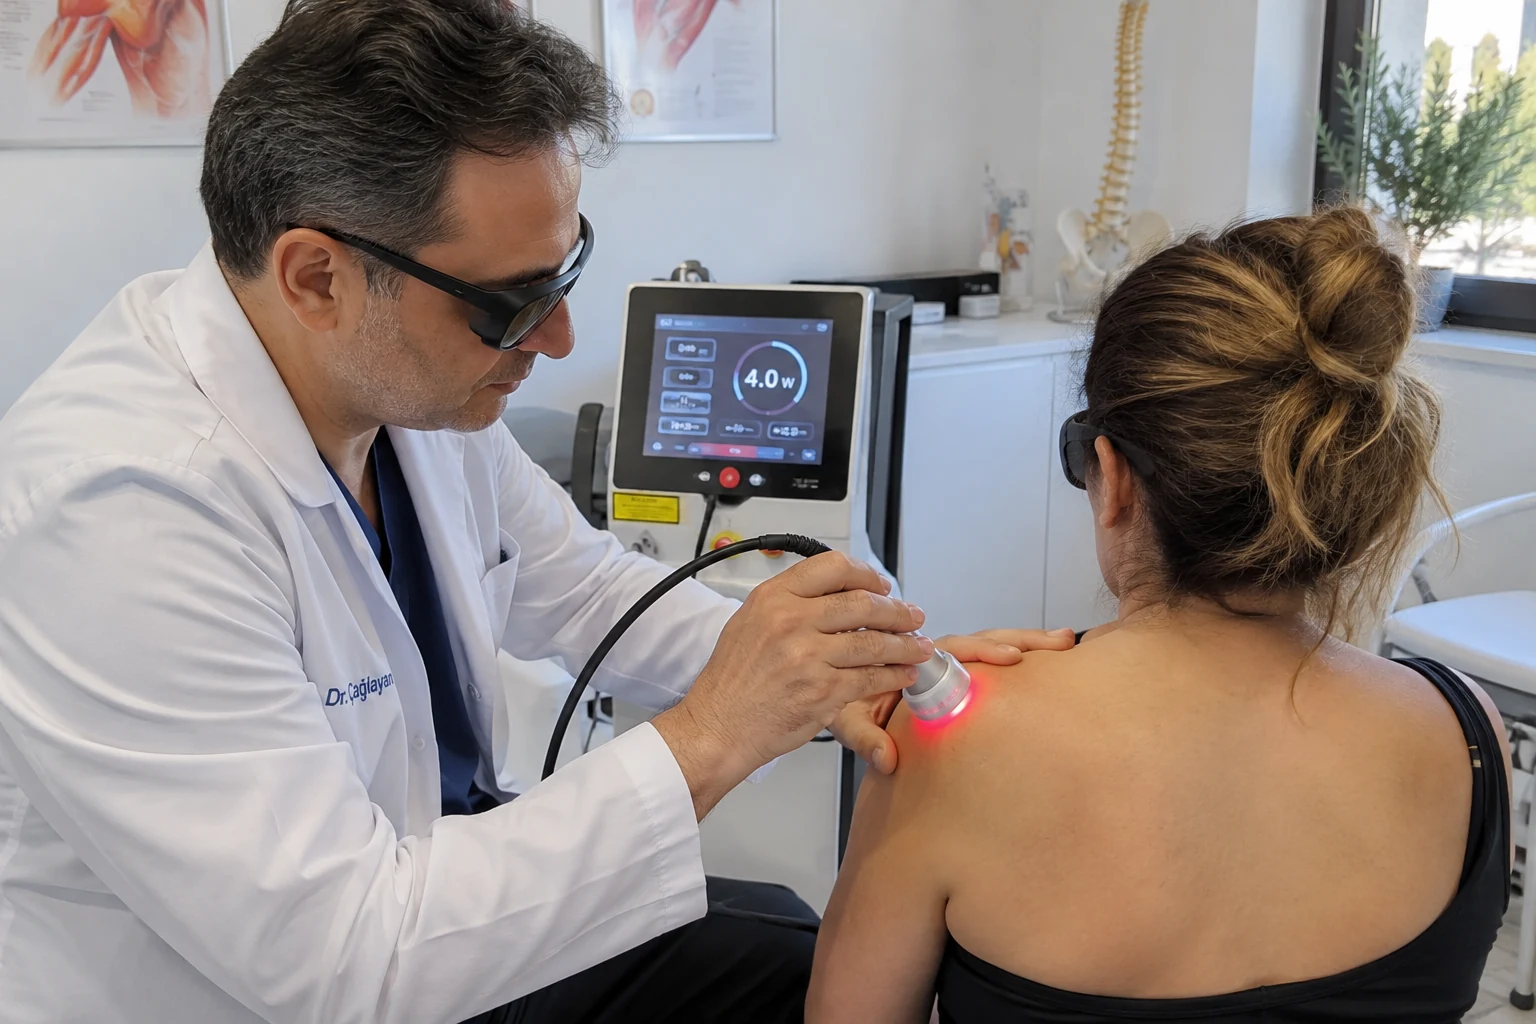
There is growing clinical data for HILT in rotator cuff tendinopathies. Current meta-analyses have reported favorable outcomes in terms of pain and disability in shoulder-related tendinopathies. In most cases, 980 nm is the primary superficial/intermediate-depth wavelength; since 1470 nm has a more superficial and thermal character, it is considered as an adjunct only in selected superficial targets.
What are rotator cuff and supraspinatus tendinopathy?
The rotator cuff is the group of tendons involved in the movement and stability of the shoulder. The supraspinatus tendon is one of the most common pain-generating structures in this group. Pain may increase when lifting the arm to the side or to the front, when lying on it at night, or with repetitive loading. It must be differentiated from conditions such as full-thickness tears, cervical-origin pain, and frozen shoulder.
How can laser help?
HILT and photobiomodulation have been investigated for analgesic effects, modulation of the local inflammatory response, and supporting peritendinous tissue metabolism. The clinical goal is to reduce pain and make controlled tendon loading more tolerable. It should not be claimed that the laser reattaches a torn tendon or corrects structural damage on its own.
The role of 980 nm
It can be considered the primary wavelength for superficial and intermediate-depth tendon/periarticular targets around the shoulder. A significant portion of the HILT literature is based on 980 nm or nearby NIR wavelengths.
The role of 1470 nm
1470 nm is absorbed more strongly by water and concentrates energy at the surface. It is not the routine primary wavelength in rotator cuff tendinopathy; it can only be a selective adjunctive option in superficial accompanying targets, taking skin safety into account.
What does the scientific evidence say?
Evidence level: A-. Randomized trials and meta-analyses in shoulder-related tendinopathies have reported favorable outcomes in terms of pain and function. However, study protocols, energy dosages, and exercise programs vary.
Is laser sufficient on its own?
In most cases, no. Isometric and isotonic loading, external rotation and elevation capacity, scapular control, and activity-specific progression are planned. Success should be monitored not only by pain scores, but also by strength and function.
Our approach in our Bodrum clinic
Our approach in our Bodrum clinic is to differentiate whether shoulder pain originates from the tendon, bursa, joint, or neck; and if rotator cuff tendinopathy is confirmed, to consider the 980 nm laser as an adjunctive method supporting controlled tendon loading. 1470 nm is used only for selected superficial targets.
When is a different evaluation required first?
In the presence of sudden loss of strength following trauma, pseudoparalysis, dislocation, a febrile swollen shoulder, or advanced neurological findings, further evaluation is required first.
Frequently Asked Questions
Does supraspinatus tendinitis resolve with laser?
Laser can reduce pain and increase exercise tolerance in some patients; gradual readjustment of tendon load is essential for lasting improvement.
980 nm or 1470 nm?
For rotator cuff targets, 980 nm is the more appropriate primary wavelength. 1470 nm is not the routine primary choice due to its superficial thermal effect.
References
- Tendinopatilerde HILT meta-analizi
- Omuz ağrısında HILT literatürü
- 810/980 nm HILT klinik çalışması
- 980/1470 nm fizik karşılaştırması
Disclaimer
This content is for general health information purposes; it is not a personal diagnosis or treatment recommendation.

