Who is it evaluated for?
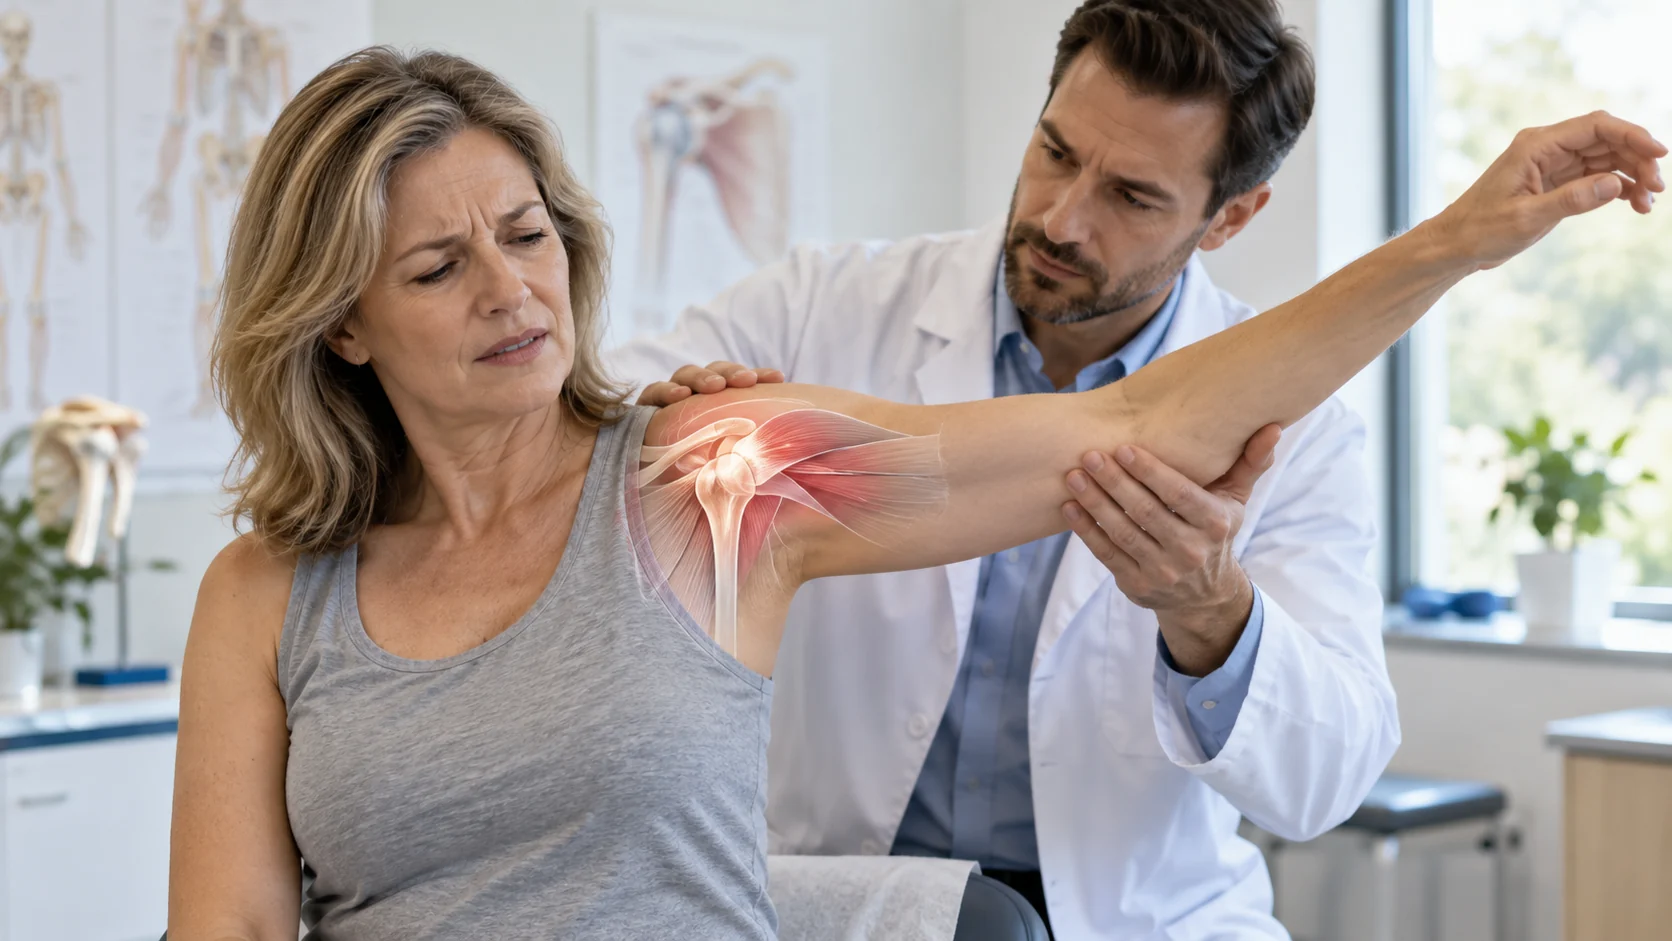
Evaluation can be beneficial for individuals who experience shoulder pain during arm elevation, dressing, lying down at night, or sports; or who feel movement restriction or a noticeable decrease in strength.
How is it planned?
Range of motion, strength, pain pattern, and neck-related findings are evaluated together. When necessary, ultrasound or MRI is added; exercise, rehabilitation, pain management, and, in appropriate cases, injections or other methods are planned tailored to the individual.
What is rotator cuff-related shoulder pain?
Rotator cuff tendons play an important role in shoulder movement and stability. The 2025 clinical practice guideline provides structured recommendations for diagnosis, nonsurgical treatment, rehabilitation, and return to work/sports in rotator cuff-related shoulder pain. It is increasingly emphasized that tendon changes seen on imaging are not always the sole source of pain and must be interpreted together with clinical evaluation.
What is frozen shoulder?
In adhesive capsulitis or frozen shoulder, both active and passive range of motion can be significantly restricted. Restriction of external rotation is particularly notable. It may be seen more frequently in diabetes and certain metabolic conditions. The course can last for months; in most individuals, significant improvement can be observed over time with nonsurgical methods.
When is imaging needed?
MRI is not necessary for every shoulder pain. In conditions such as trauma, marked loss of strength, suspicion of a full-thickness rotator cuff tear, persistent significant complaints despite treatment, or surgical planning, ultrasound or MRI may be more meaningful. X-rays can be useful for osteoarthritis, calcification, and certain bone pathologies.
Exercise and rehabilitation
The 2025 rotator cuff guideline addresses active, personalized rehabilitation as one of the primary treatment components. Strengthening the muscles around the shoulder and scapula, movement control, and progressive loading can be planned according to the individual’s symptoms. In frozen shoulder, range-of-motion exercises should be adjusted based on the stage of the disease and the level of irritability.
Medications and injections
Short-term analgesic or anti-inflammatory treatments may facilitate pain management in some patients. Corticosteroid injections can provide short-term relief, especially during specific phases of rotator cuff-related pain or frozen shoulder. The decision to inject should be made together with diabetes, tendon status, infection risk, and other clinical factors.
PRP and regenerative options
PRP and similar biologic applications are being investigated in rotator cuff tendinopathy and certain tendon problems. Although positive results have been reported in studies, there are differences among preparation protocols, injection techniques, and patient selection. For this reason, the extent to which they may contribute to a particular shoulder problem should be evaluated in an individual clinical context.
Ozone and other complementary methods
Ozone and various local complementary applications are used and investigated in musculoskeletal pain. Current clinical experience and studies in shoulder pain may suggest that there could be benefit in certain patient groups; however, making the correct primary diagnosis and linking the application with main treatment components such as exercise/rehabilitation is important.
When is a more urgent evaluation needed?
- Inability to move the shoulder after severe trauma
- New and marked arm weakness
- Redness, warmth, and fever in the shoulder
- New deformity or suspected dislocation
- Shoulder pain accompanied by chest pain, shortness of breath, or systemic symptoms
Our approach in our Bodrum clinic
We do not evaluate shoulder pain solely under the label of “tendon tear” or “osteoarthritis.” The neck, scapula, rotator cuff, joint capsule, and daily loading are examined together. Movement and function are kept at the center of the treatment plan; imaging, injection, or interventional options are added according to clinical necessity.
For the general pain approach, you can review the Pain Management guide.
References
- Desmeules F, et al. Rotator Cuff Tendinopathy Diagnosis, Nonsurgical Medical Care, and Rehabilitation: A Clinical Practice Guideline. J Orthop Sports Phys Ther. 2025. PMID: 40165544.
- Lee BC, et al. Clinical Practice Guidelines for Diagnosis and Non-Surgical Treatment of Primary Frozen Shoulder. Ann Rehabil Med. 2025. PMID: 40602400.
- Zhang B, et al. Addressing Shoulder Weakness in Individuals With Rotator Cuff-Related Shoulder Pain: A Systematic Review With Meta-analysis. 2026. PMID: 41620837.
Written and medically reviewed by: Dr. Kerem Çağlayan
Last medical review: September 10, 2026
Disclaimer: This content is general health information; it is not a personalized diagnosis or treatment recommendation.