
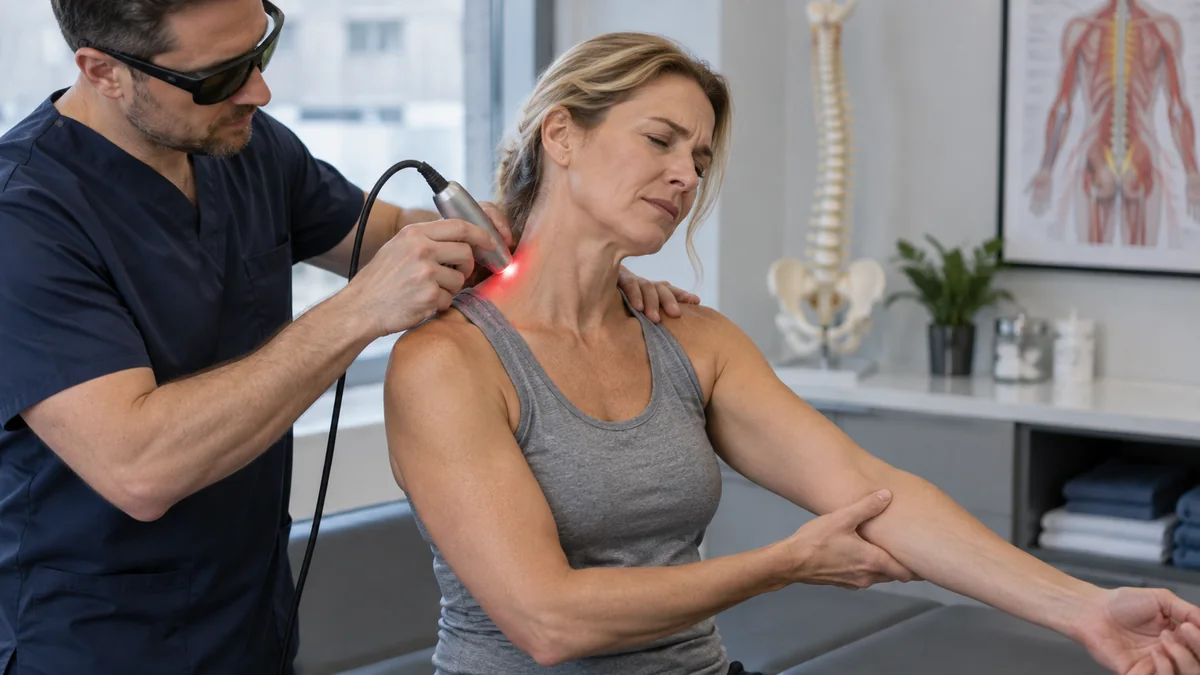
What is cervical radiculopathy?
Irritation of the cervical nerve root due to causes such as cervical disc herniation, degenerative changes, or foraminal narrowing can lead to pain radiating from the neck to the shoulder and arm, numbness, tingling, and sometimes loss of strength. Because similar complaints can also originate from the shoulder, peripheral nerves, or myofascial structures, a neurological examination is important.
How can laser help?
In HILT and photobiomodulation studies, effects on pain modulation, local inflammatory response, and tissue metabolism have been investigated. The clinical goal is to reduce pain and increase movement and exercise tolerance. Laser should not be presented as a method that shrinks disc herniation or removes mechanical compression on the nerve.
The role of 980 nm
It can be considered as the primary wavelength for paravertebral and periarticular soft tissue targets, as well as for muscle spasms accompanying nerve root pain. A significant portion of the HILT literature comes from 980 nm or nearby NIR wavelengths.
The role of 1470 nm
1470 nm concentrates energy more superficially. It should not be viewed as a routine primary wavelength in cervical radiculopathy; it should only be considered as an adjunctive option for superficial accompanying muscle-fascia targets, with careful monitoring of skin temperature.
What does the scientific evidence say?
Level of evidence: A- — direct clinical evidence exists, but heterogeneity and protocol differences are present. Systematic reviews/meta-analyses for spinal radiculopathy report that HILT may provide an adjunctive contribution to pain and function. Findings are supportive; the same result should not be expected in every patient.
Is laser sufficient on its own?
In most cases, no. It is planned together with muscle strength, sensory, and reflex examinations; cervical and scapular exercises, nerve mobilization when necessary, medical therapy, imaging, and interventional options in appropriate patients.
Our approach in our Bodrum clinic
Our approach in our Bodrum clinic is to first determine whether the pain radiating to the arm genuinely originates from the cervical nerve root, and then to evaluate the use of 980 nm or, in selected superficial areas, 1470 nm according to the depth of the target tissue. We treat the procedure not as a device-focused single treatment, but as part of rehabilitation and, when necessary, interventional pain treatments.
When is a different or urgent evaluation required first?
In cases of progressive hand-arm weakness, rapid deterioration in manual dexterity, gait imbalance, widespread numbness, or signs of myelopathy, the priority is advanced evaluation.
Frequently asked questions
Does a cervical disc herniation improve with laser?
Laser may support pain and functional tolerance in some patients; however, it cannot be said to mechanically eliminate disc herniation or nerve compression.
Which wavelength is preferred for pain radiating to the arm?
For superficial/intermediate-depth soft tissue targets, 980 nm is a more rational primary option. 1470 nm may be helpful for selected superficial accompanying targets.
How many sessions are administered?
There is no fixed number of sessions. Neurological findings, duration of pain, and response to initial applications are taken into account.
References
- Systematic review and meta-analysis of HILT in spinal radiculopathy
- Clinical literature on laser therapy in neck pain
- Physical comparison of 980 and 1470 nm wavelengths
Information
This content is for general health information purposes. Suitability is determined by the physician based on neurological examination, diagnosis, and target anatomy.

