What does this score mean?
The Trust Index is not a treatment success rate; it is an editorial methodology score indicating to what extent the scientific finding evaluated on this page can be trusted. Study design, risk of bias, sample size, precision, direct applicability, reproducibility, transparency, and clinical significance are evaluated together.
What did the study investigate?
It evaluated the importance of early diagnosis, initiation of DMARDs within the first weeks, and the treat-to-target approach on clinical outcomes in rheumatoid arthritis.
How was it done?
A current clinical review published in JAMA and existing international treat-to-target principles were synthesized.
What was found?
Early diagnosis and not delaying disease-modifying therapy, clear response at month 3, and targets of remission/low disease activity at month 6 stand out.
Limitations of the study
This is not a single-intervention RCT; it is a clinical review synthesizing broad literature and guideline approaches. Individual treatment selection varies according to comorbidities and risk profile.
What does it mean clinically?
Not delaying treatment in inflammatory joint findings and performing early rheumatology evaluation are strongly supported clinically.
What do we not know yet?
The optimal DMARD sequence, biologic/JAK inhibitor choice, and long-term risk-benefit balance in an individual patient require personalized evaluation.
Source
The full citation and links of the sources are preserved in the detailed evaluation section of this page.
Written and medically reviewed by: Dr. Kerem Çağlayan · Information about pain · All Scientific Research
Detailed evaluation
Research evaluation · September 12, 2026
A current clinical review published in JAMA on September 10, 2026, re-emphasizes the importance of early diagnosis and the treat-to-target approach in rheumatoid arthritis. In particular, the first 6 weeks after symptom onset stand out as a critical clinical window for preventing irreversible joint damage.
Why are the first 6 weeks important?
Rheumatoid arthritis is a chronic autoimmune disease in which synovial inflammation can progress over time to irreversible damage in cartilage and adjacent bone. The JAMA review recommends that diagnosis be made preferably within 6 weeks after symptom onset and that disease-modifying antirheumatic drugs (DMARDs) be initiated promptly.
The clinical implication of this window is this: reducing pain and controlling disease activity are not the same thing. NSAIDs, short-term glucocorticoids, or other symptomatic approaches may reduce pain; however, they may not sufficiently control synovitis and the risk of joint damage on their own.
Which findings should suggest early referral?
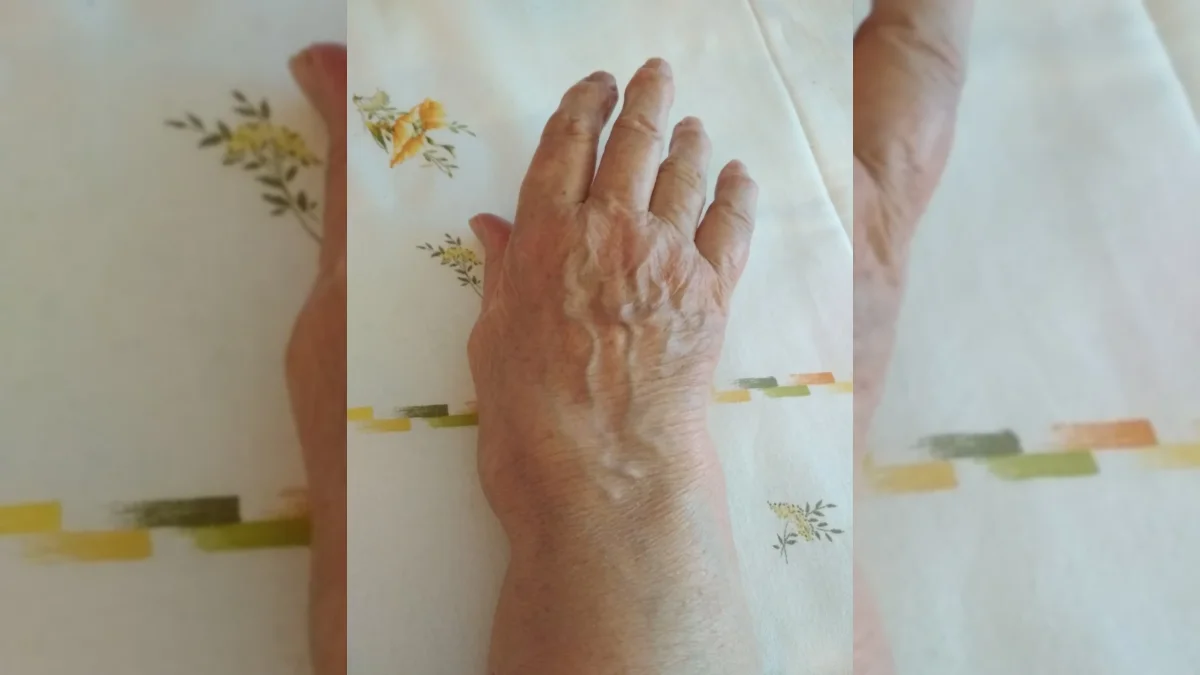
- Swelling in metacarpophalangeal, proximal interphalangeal, or wrist joints
- Symmetric small joint involvement
- Prolonged morning stiffness
- Inflammatory picture consistent with elevated CRP/ESR
- Rheumatoid factor or anti-CCP positivity
- Symptoms lasting for several weeks and progressively increasing
Rheumatoid factor or anti-CCP negativity does not completely rule out RA. The diagnosis is established in conjunction with history, joint examination, laboratory tests, and imaging when necessary.
What are the treatment targets?
In the current treat-to-target approach, the goal is not merely “feeling a bit better.” The target is to achieve at least a 50% improvement in disease activity at month 3 and remission or low disease activity at month 6.
According to the review, approximately 40% of newly diagnosed patients can achieve CDAI remission within the first 6 months. In patients who do not achieve the target with first-line DMARD therapy, the addition of a biologic DMARD or, in appropriate patients, a JAK inhibitor can raise the rate of remission or low disease activity to approximately 80%.
Why does methotrexate stand out in the first line?
Methotrexate continues to be the primary initial DMARD in most patients. However, before initiation, the possibility of pregnancy, severe hepatic disease, cytopenia, renal function, and concomitant medications should be evaluated. CBC, creatinine, and transaminase monitoring along with folate supplementation are part of the standard safety approach.
If glucocorticoids are needed, they should be used for the shortest duration possible and, as recommended in the review, preferably tapered and discontinued within 3 months.
Are JAK inhibitors suitable for everyone?
No. In patients at high risk for thromboembolism, cardiovascular events, or malignancy, the benefit-risk balance of JAK inhibitors must be carefully evaluated. Therefore, treatment selection should be made not only based on disease activity, but also according to age, comorbidities, and the individual risk profile.
Message for pain and functional medicine practice
Applicable now. Treating an inflammatory joint pattern as mechanical or nonspecific pain and losing weeks with trials of supplements, diet, or analgesics is not appropriate. Functional medicine and lifestyle approaches can support accompanying metabolic, sleep, or quality-of-life goals; however, they cannot replace disease-modifying therapy in active rheumatoid arthritis.
Especially in patients with symmetric small joint swelling and morning stiffness, early rheumatology evaluation is one of the most critical steps in preventing treatment delay.
Quality of evidence
High. This content is based on a JAMA clinical review synthesizing current diagnostic and treatment principles and is consistent with the current international treat-to-target approach.
Reference
Smolen JS, Kerschbaumer A, Aletaha D, Robinson WH. Rheumatoid Arthritis in Adults: A Review. JAMA. Published online September 10, 2026.
Image: Hand affected by rheumatoid arthritis; Amm0nium/Wikimedia Commons, CC BY-SA 4.0.